
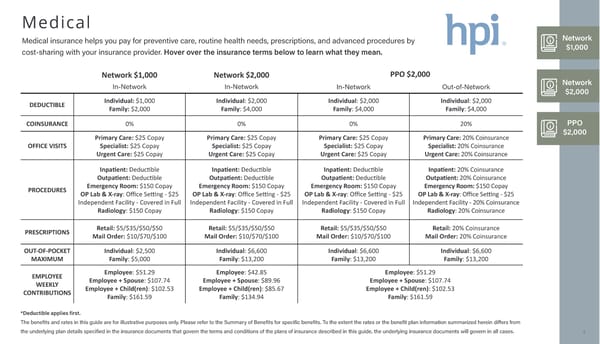
4 Medical Medical insurance helps you pay for preventive care, routine health needs, prescriptions, and advanced procedures by cost-sharing with your insurance provider. Hover over the insurance terms below to learn what they mean. *Deductible applies first. The benefits and rates in this guide are for illustrative purposes only. Please refer to the Summary of Benefits for specific benefits. To the extent the rates or the benefit plan information summarized herein differs from the underlying plan details specified in the insurance documents that govern the terms and conditions of the plans of insurance described in this guide, the underlying insurance documents will govern in all cases. Network $1,000 Network $2,000 PPO $2,000 Network $1,000 Network $2,000 In-Network PPO $2,000 In-Network In-Network Out-of-Network DEDUCTIBLE Individual: $1,000 Individual: $2,000 Individual: $2,000 Individual: $2,000 Family: $2,000 Family: $4,000 Family: $4,000 Family: $4,000 COINSURANCE 0% 0% 0% 20% Primary Care: $25 Copay OFFICE VISITS Specialist: $25 Copay Urgent Care: $25 Copay Primary Care: $25 Copay Specialist: $25 Copay Urgent Care: $25 Copay Primary Care: $25 Copay Specialist: $25 Copay Urgent Care: $25 Copay Primary Care: 20% Coinsurance Specialist: 20% Coinsurance Urgent Care: 20% Coinsurance PROCEDURES Inpatient: Deductible Outpatient: Deductible Emergency Room: $150 Copay OP Lab & X-ray: Office Setting - $25 Independent Facility - Covered in Full Radiology: $150 Copay Inpatient: Deductible Outpatient: Deductible Emergency Room: $150 Copay OP Lab & X-ray: Office Setting - $25 Independent Facility - Covered in Full Radiology: $150 Copay Inpatient: Deductible Outpatient: Deductible Emergency Room: $150 Copay OP Lab & X-ray: Office Setting - $25 Independent Facility - Covered in Full Radiology: $150 Copay Inpatient: 20% Coinsurance Outpatient: 20% Coinsurance Emergency Room: $150 Copay OP Lab & X-ray: Office Setting - $25 Independent Facility - 20% Coinsurance Radiology: 20% Coinsurance Retail: $5/$35/$50/$50 Retail: $5/$35/$50/$50 Retail: $5/$35/$50/$50 Retail: 20% Coinsurance PRESCRIPTIONS Mail Order: $10/$70/$100 Mail Order: $10/$70/$100 Mail Order: $10/$70/$100 Mail Order: 20% Coinsurance OUT-OF-POCKET Individual: $2,500 Individual: $6,600 Individual: $6,600 Individual: $6,600 MAXIMUM Family: $5,000 Family: $13,200 Family: $13,200 Family: $13,200 EMPLOYEE WEEKLY CONTRIBUTIONS Employee: $51.29 Employee + Spouse: $107.74 Employee + Child(ren): $102.53 Family: $161.59 Employee: $42.85 Employee + Spouse: $89.96 Employee + Child(ren): $85.67 Family: $134.94 Employee: $51.29 Employee + Spouse: $107.74 Employee + Child(ren): $102.53 Family: $161.59
 2027 Benefits Guide Page 3 Page 5