
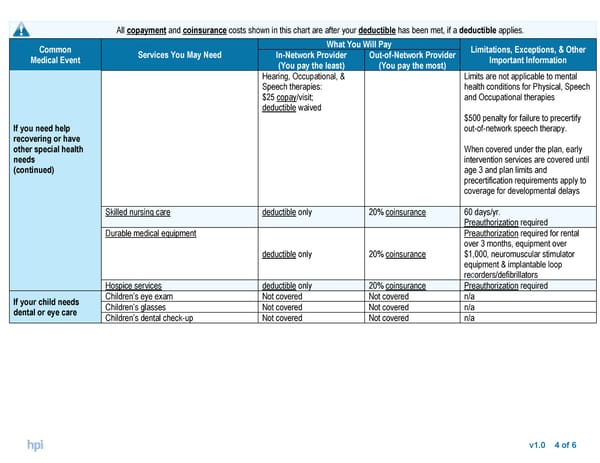
v1.0 4 of 6 All copayment and coinsurance costs shown in this chart are after your deductible has been met, if a deductible applies. Common Medical Event Services You May Need What You Will Pay Limitations, Exceptions, & Other Important Information In-Network Provider (You pay the least) Out-of-Network Provider (You pay the most) If you need help recovering or have other special health needs (continued) Hearing, Occupational, & Speech therapies: $25 copay/visit; deductible waived Limits are not applicable to mental health conditions for Physical, Speech and Occupational therapies $500 penalty for failure to precertify out-of-network speech therapy. When covered under the plan, early intervention services are covered until age 3 and plan limits and precertification requirements apply to coverage for developmental delays Skilled nursing care deductible only 20% coinsurance 60 days/yr. Preauthorization required Durable medical equipment deductible only 20% coinsurance Preauthorization required for rental over 3 months, equipment over $1,000, neuromuscular stimulator equipment & implantable loop recorders/defibrillators Hospice services deductible only 20% coinsurance Preauthorization required If your child needs dental or eye care Children’s eye exam Not covered Not covered n/a Children’s glasses Not covered Not covered n/a Children’s dental check-up Not covered Not covered n/a
 Summary of Benefits and Coverage: Life Is Good PPO $2,000 Plan Page 3 Page 5